The Cardiosense CardioTag is a noninvasive, wearable cardiac monitor with FDA 510(k) clearance. [Image courtesy of Cardiosense]
Martin is now the portable ultrasound company’s chief medical officer emeritus, and just started as EVP and chief medical officer at cardiac sensor developer Cardiosense.
Cardiosense has developed an artificial-intelligence-powered wearable with sensors for not only electrocardiogram (ECG) data to measure the heart’s electrical activity, but also seismocardiogram (SCG) data tracking cardiogenic vibrations of the chest wall from the heart’s contraction and blood movement, and photoplethysmogram (PPG) data that captures changes in blood volume with each heartbeat.
We spoke with Martin ahead of the official announcement of his new role to discuss Cardiosense’s technology, the tech that makes it possible, and what he’s learned in his career in medicine and medtech.
The following has been lightly edited for space and clarity.
What’s so special about what Cardiosense is doing, and what technology is enabling that? Is it primarily the software, or are you using any advanced sensors?

Cardiosense says its CardioTag device is the first multimodal, wearable sensor that simultaneously captures high-fidelity electrocardiogram (ECG), photoplethysmogram (PPG), and seismocardiogram (SCG) signals. [Image courtesy of Cardiosense]
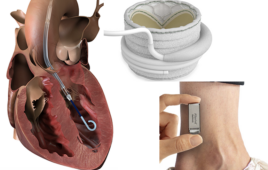
“Then the next phase came, and companies made implanted sensors like CardioMEMS or Cordella at Edwards. They put a sensor inside the body because we know pressure measurements matter. Let’s find a better way to do that. They’ve been very successful in showing that it has value: reduced ED visits, reduced hospitalizations. The downside is adoption rates have been very poor, less than 10%. Why? Because it’s expensive and it’s invasive, and people generally don’t like stuff stuck in them if they can avoid it.
“So then you have the next kind of evolution, if you will. Butterfly has shown pretty nicely that monitoring congestion using ultrasound B-lines has been incredibly effective. … That’s great if you’ve got people with a Butterfly in hand that can do that. I think that’s fantastic. That’s been a big advance, and I’ve been really excited to be part of that. But ultimately, it still requires a professional with a probe in their hand to do this. Where you ultimately want to get to is to plop something on somebody’s body that’s a wearable, easy to use and can spit out a number that makes it easy.
“Lo and behold, there is Cardiosense, which has developed this lovely little device. It’s part device and part software. The device itself has three different sensors that are incredibly important: ECG, PPG, and now SCG, something that’s a little less familiar to everyone, seismocardiography. If you talk to the veterans in cardiology, they’ll say they knew about SCG and that, in and of itself, wasn’t so great. But what’s different here, and what’s very special about the world’s experts that are basically the scientists behind this, they’ve coupled together those three signals then leverage the hottest thing in the world right now — artificial intelligence tools — put those three signals, the advanced accelerometers that are there now to pick up those very subtle vibrations of the heart (that’s what SCG is) with now an AI tool. Now you’ve got something that can predict accurately a pulmonary capillary wedge pressure and match the accuracy, at least in the early studies of a CardioMEMS implantable device at a fraction of the cost without it being an implantable.”
Min-Vasive Medtech: Watch live interviews and audience Q&As with minimally invasive engineers from Edwards Lifesciences, Jupiter Endo and Compremium
You’re starting with heart failure, but it sounds like there’s lots of opportunity for more with this technology?

Cardiosense EVP and Chief Medical Officer Dr. John Martin [Photo courtesy of Cardiosense]
“The next phase of this is the Seismic 2 trial that’s going on right now where they’re looking at that accuracy in heart failure patients with reduced ejection fraction to get the algorithm then cleared by the FDA. I think they were incredibly smart to bifurcate those two things. Not often is that done. But it gives you the ability to have an FDA-cleared device to start doing a host of different studies where at least you’re capturing observational data to see is it going to be effective in all these other use cases, not just in reduced ejection fraction, but in preserved ejection fraction, in all the different clinical environments whether it’s the hospital, the clinic, home, in a nursing home, pick your venue. And you can start opening up the aperture, if you will, into the other settings in which It’s useful. The other medical chronic condition that consumes a ton of money that’s all about volume. It’s renal failure. We’ve got hundreds of thousands of people on dialysis three times a week. It’s all about volume, and we do it based on dry weight, which is a crappy measure and everybody knows it, but it’s the best that we have. If you now have a device that you could plop on their chest that tells you when the right amount of volume is coming off and it dings just like your microwave, you could certainly imagine how much better dialysis is going to go and how much better patients will able to manage themselves at home if they’ve got a device to know they better back off their fluids, basically having their own gas gauge. What an incredibly powerful thing that could be. If you look at trauma and volume resuscitation, incredibly important. You look at sepsis, where hypotension is there, do you need better contractility, or you need more afterload, or more preload? So as you start thinking about where the opportunities of this device are, it’s pretty exciting.”
Nitinol innovation: Download our free special report featuring nitinol expertise and tips from medical device OEMs working in the heart and elsewhere
So the idea is eventually this could be mailed to someone’s home and the patient sticks it and forgets it?
Martin: “You don’t have to wear it all the time. You don’t have to measure it constantly. You need to do it under a physician supervision. But step back for a moment. Where were glucose monitors when they first started? Done in the hospital by a medical expert who had to sit there and read the results with special training. Where is it today? Completely different world. I don’t think it’s that far-fetched to see that world coming for this. Obviously, a lot more work’s got to be done. We don’t want to get ahead of our skis, but it’s pretty easy to imagine if you can get that kind of predictability — and the data certainly suggests that it could be accurate — there’s a world in which the day-to-day lives of heart failure patients could change dramatically.”
What kind of timelines does Cardiosense have to get some of these things done?
Martin: “We’ve got FDA clearance right now for the device. We’re in the middle of the trial right now for the algorithm itself. We should get that done this year, submit to the FDA, and we hope to have clearance of that algorithm and kind of emerge into the market in 2026. And we’ll start doing work right now on clinical studies in these other environments to build the datasets that will be necessary to both give the commercial-end payers the justification as to why they should be investing in this technology, as well as opening up that aperture in other places. The end of this year and next year are going to be pretty busy for us.”
What are the most important things you’ve learned in your career that you’re going to bring to your new role at Cardiosense?
Martin: “First of all, the data is important. You have to have the clinical credibility of the data itself to convince physicians that this is valid. But it’s not just that. You can think about all the applications that are out there. Radial artery angioplasty, for instance, was 90% of the cases in Europe and Asia before it ever came to United States, and we were slow to adopt it here. Even Butterfly — tremendous device, incredibly useful and expanding — but is everybody using it? No, even though we know that it’s better. Why is that? Because we’re incredibly slow in healthcare to change what we do, and it’s about changing human behavior. The biggest thing I’ve learned is how to change physician behavior, the most effective way to do that. Far and away, it means you can’t have any resistance to adoption. It has to fit into care flow seamlessly so it just becomes natural. I’m just going to plop it on, it’s not going to make my day longer, it’s not going to be harder for me, not going to require any extra work for me. And, oh, by the way, I’m going to get value out of this so it’s worth it to me. That’s probably been the most valuable lesson. I think some of it is patience. Even though you can look at it, get excited and say, ‘Geez, doc, can’t you see this? This is great. ‘Not everybody sees it like you see it and change is not going to happen instantly, no matter how obvious you think it is that it’s better. It takes time, and to have that kind of patience becomes incredibly important. It’s also knowing what’s the right influence to go about. It’s kind of an interesting way to think about the way in which we’ve influenced behavior in healthcare. If you’re familiar with Michael Porter’s Five Forces, it’s all about the beginning of new technology into the world. I’ve kind of adjusted a little bit to think about how do we bring new technology into being? This is John Martin’s adoption of Michael Porter’s Five Forces. How do things come in? First of all, there’s the government and payers. The government mandated an EHR. Why is it an electronic record used everywhere? It isn’t because we like it. It isn’t because anybody likes it. It’s because the government said, ‘Thou shalt.’ And payers are the same way. ‘You can use this technology and I’ll approve it. If not, I won’t.’ So that’s one end. You get on the other end of that circle, and it’s institutional. The institution says you should use it, or you will use it. Or if you look at different medical devices that you cover, you can use Medtronic’s, but not Edwards’, because we have a contract with Medtronic. So you can influence adoption if the institution mandates that. If the institution says you will do and use this because it’s been shown to reduce hospitalizations, it will change inside that institution. Then you get at the top, and then you have the literature and the professional societies. In this situation, what does the ACC say, what does the AHA say, what guidelines are actually out there that drive behavior, that set what the standard of care is, and what does the literature show? That’s a driver. At the bottom, it’s the peers. What do your colleagues do? Back when laparoscopic cholecystectomy started, it wasn’t an academic institution, it was the guys out in the community. Dr. Eddie Joe Reddick in South Carolina was doing these things, his patients were doing better, and people go, ‘Wait a minute. I’m losing all my cases to him because it’s better.’ How did robotics grow, how did laser grow? It was competition between hospitals, because cases move quickly, and it was the KOLs and the influencers in the community that said, ‘This is better. I’m going to show you. I’m going to take your business away.’ That drove things. So those are the big four around the outside. The one in the middle is the patients. Where did the pharmaceutical companies go when they realized that they couldn’t go through their drug reps into the doctor’s offices to influence behavior? What are they doing? Direct to consumer. You see ads all day long. The way I think about this, what I’ve learned along the way is we have to have a strategy for all five. Work with the professional societies, develop the peer literature, work with the payers that show there’s a value to them from a clinical and economic perspective. Get into the institutions and show them why it’s got great value to them. Develop key opinion leaders that can influence other’s behavior along the way, and then eventually you get to the patients themselves. Once you have all the right clearances and the data, say, ‘You tell your doctor you want one of these.’ The beautiful thing about Cardiosense’s device, called CardioTag right now, is you can certainly see the market: ‘Get tagged.’ ‘I want to be tagged.’ ‘You want to know what your volume is? Get tagged.” You can see that will grow in the emergency room and throughout the hospital. ‘Throw a tag on them. We want to know what the volume is on this patient and we’ll treat them.’ That’s the opportunity that lays in front of us, and it’s pretty exciting.
Any advice for our readers to better understand user needs when they’re developing products?
Martin: “You’ve got to live in the shoes of the doctors for a bit and see what their world is like. There’s a lot of sales that’s muscle. You muscle your way through, you’re persistent. You’ve got to understand the line between persistence and annoyance when you’re dealing with clinicians. But I think the better that you can appreciate the clinical environment in which it’s used and the clinicians that are using it and what’s important to them, at the end of the day I think about solving problem. With new technology, first of all, you have to have a problem that people feel and can immediately identify with … and appreciate. If there’s a nuance of explaining the problem, you’re dead in the water. The second thing is, there’s got to be an economic value to it, particularly in this day and age where margins are so thin. Does it generate revenue? Does it save money? Does it save time? Is there an economic story that justifies the cost of the device for an institution to invest in it at this time? Because they’ve got limited resources so does it make economic sense? Does it make clinical sense? Can I actually feel the tangible clinical benefits of this that become obvious, or is this something I’m going to invest in and 10 years from now you’re going to see the benefit. … You need immediate feedback if you want to accelerate adoptions: ‘I did this. This is what I saw. Therefore it has value.’ If you can start with those three things, then how does it fit into the workflow? Make sure what you do has no resistance to adoption. If you do those things, you’re going to be off to a good start. And I always think about who wants it, who needs it, who buys it, who pays for it, and who benefits from it? If I can answer those questions with my technology and people can look at it and say, ‘Yes, I get it,’ then the novelty becomes a key issue — you’ve got IP and all those other things. But the bottom line is if you can’t solve those ones upfront, you’re not going to be successful.”
Anything else you’d like to add before we wrap?
Martin: “I’m really excited about having the opportunity to work with creative people. I think the other thing that’s very special about Cardiosense is it’s an incredible group of really smart people, and I think that matters a great deal, if you’ve got the right kind of people that are willing to invest the right kind of time and energy in the company. They also know what they don’t know, which is another welcome thing, that they said, we need these different people coming in. They’ve welcomed me and the clinical expertise is there. I don’t think you can develop new, good medical technology unless you have medical people intimately involved. I still practice. I think that’s been one of the most important things. I don’t practice a ton, but enough that I’m side by side with my colleagues. I can feel their pain. I’ve lived the problems that are out there in healthcare, and I’ve had the beauty of sitting in almost every chair. I’ve been a patient, I’ve been the doctor, I’ve been the executive, I’ve been the president of a company, and I think that perspective gives me a very unique approach to be able to help. I’m also smart enough to know there’s a hell of a lot I don’t know, that I can learn from this team and I can learn from other people, and it’s part of why I enjoy being involved still with Butterfly and with this company, because I’ve got ways to learn from both that can help each other.”